CMS Finalizes 2024 Physician Fee Schedule: Embracing the Future with Extended Remote Supervision
The Centers for Medicare & Medicaid Services (CMS) announced a significant update on Nov 2, 2023, finalizing the 2024 Physician Fee Schedule. This rule, effective Jan 1, 2024, extends the allowance for remote supervision in healthcare services through audio/visual telecommunications until Dec 31, 2024.

Tether Supervision
Legal & Regulatory

Update: For the most current rules and state-by-state updates, visit the Tether Supervision National Policy and Regulation Tracker for Contrast Supervision.
Introduction
In a landmark decision on November 2, 2023, the Centers for Medicare & Medicaid Services (CMS) released the final Calendar Year (CY) 2024 Physician Fee Schedule (PFS). This highly anticipated rule, effective from January 1, 2024, cements the pivotal shift towards expanded use of remote supervision in healthcare, a transformation largely catalyzed by the COVID-19 pandemic.
Background
The concept of "direct supervision," traditionally requiring the physical presence of a supervising professional during certain medical procedures, saw an innovative evolution during the pandemic. With the introduction of the Calendar Year 2024 Physician Fee Schedule Proposed Rule in July 2023, CMS proposed extending the use of remote supervision, allowing "direct supervision" via audio and visual interactive telecommunications through December 31, 2024.
The Final Rule
The finalized rule confirms this extension, highlighting CMS's recognition of the effective and safe application of remote supervision during the Public Health Emergency (PHE). The rule specifies that direct supervision can now be provided through real-time audio/visual communication technology, excluding audio-only methods. This extension reflects a continued commitment to improving healthcare accessibility and acknowledges the efficacy of telehealth services.
Implications and Future Outlook
This extension is more than a temporary adjustment; it symbolizes a potentially permanent shift in healthcare practices. The decision to extend virtual direct supervision until the end of 2024 opens up new avenues for patient care, especially in rural and underserved areas where healthcare accessibility has traditionally been a challenge.
CMS's move also aligns with other telehealth-related policies enacted during the pandemic, indicating a broader trend towards integrating digital technology in healthcare. The extended policy ensures continuity of care and mitigates logistical challenges for healthcare providers and patients alike.
Conclusion
The CY 2024 PFS Final Rule by CMS marks a significant step in the evolution of healthcare delivery. While the policy is currently set until the end of 2024, CMS's ongoing evaluation hints at a future where remote supervision could become a permanent fixture in healthcare. As the industry adapts to these changes, the focus remains on ensuring patient safety and quality of care in this new era of digital healthcare.
For more detailed information on the Medicare Physician Fee Schedule Final Rule, resources such as the official CMS Final Rule, Press Release, and Fact Sheet are available for reference.

Take the uncertainty out of contrast supervision.
We’ll support your team every step of the way, from onboarding and training to live supervision and ongoing quality improvement.
Take the uncertainty out of contrast supervision.
We’ll support your team every step of the way, from onboarding and training to live supervision and ongoing quality improvement.
Read more from Tether Supervision
Tether is the leading platform for virtual contrast supervision, built for speed, safety, and seamless imaging operations.
Expert perspectives on safe, efficient contrast workflows and clinical readiness.
Tether is the leading platform for virtual contrast supervision, built for speed, safety, and seamless imaging operations.

Washington HB 2113 Signed: Virtual Supervision Now Law | What’s Next for DOH & Imaging Centers
Washington State has officially taken a major step forward in modernizing radiologic technologist supervision. House Bill 2113 has now been signed into law following overwhelming bipartisan support, marking a meaningful shift in how imaging centers can deliver care, maintain access, and deploy physician resources. Earlier this year, we outlined the growing momentum behind this legislation and its potential impact on the industry. With the bill now enacted, the conversation shifts from possibility to implementation.
At its core, HB 2113 formally allows intravenous contrast procedures performed by radiologic technologists to be supervised through real-time, two-way audio and video technology. This effectively introduces virtual direct supervision into Washington law, aligning the state with permanent federal CMS policy and removing one of the most persistent operational constraints in outpatient imaging. In parallel, the bill expands on-site supervision options by allowing advanced practice registered nurses and physician assistants to supervise IV contrast procedures under direct supervision, addressing long-standing access challenges in emergency departments and rural settings. Importantly, the legislation maintains a clear expectation that trained clinical personnel and appropriate emergency response capabilities remain physically present at the facility, reinforcing that virtual supervision enhances—but does not replace—on-site patient care readiness.
The law is set to take effect 90 days after adjournment of the legislative session, placing practical implementation in mid-2026. At that point, the statute becomes controlling, and imaging centers will have a clear legal pathway to begin structuring compliant virtual supervision programs. However, the passage of the law is not the final step in the regulatory process. The Washington Department of Health will now play a critical role in aligning existing administrative rules with the new statute. Current Washington Administrative Code definitions of direct supervision still assume physical on-site physician presence, which is now partially outdated. As a result, DOH will need to undertake rulemaking to update supervision definitions, incorporate virtual supervision into formal guidance, and clarify operational expectations.
This rulemaking process typically unfolds over several phases, including initial guidance, proposed rule updates, public comment, and final adoption. In most cases, this takes six to twelve months or longer. As a result, a transitional period is expected where the statute permits virtual supervision, but formal DOH rules have not yet fully caught up. During this window, the statute governs, meaning imaging centers can move forward if they align closely with the law’s requirements and maintain strong clinical and compliance protocols.
In practice, some organizations will move quickly once the law becomes effective, leveraging the statutory authority to improve access, reduce delays, and stabilize operations. Others will take a more conservative approach, waiting for additional DOH clarification before implementing changes. Both approaches are understandable, but the underlying reality remains the same: the legal framework enabling virtual supervision will be in place as of mid-2026.
For imaging centers, HB 2113 enables more consistent coverage, reduces dependence on physical radiologist presence, and supports continued access to contrast-enhanced imaging—particularly in underserved or capacity-constrained environments. More broadly, it reflects a structural shift in how supervision is defined and delivered. Virtual supervision is no longer a temporary accommodation or regulatory exception; it is becoming a permanent and integrated component of modern imaging operations.
The passage of HB 2113 signals that Washington is now firmly aligned with this national transition. The remaining variable is not whether virtual supervision will be adopted, but how quickly organizations choose to implement it.
How Tether Can Support Your Virtual Supervision Program
Passing legislation is one thing. Implementing it safely and consistently across real clinical environments is something else entirely.
As imaging centers begin to evaluate what HB 2113 means for their operations, the real work starts at the intersection of policy, patient care, and day-to-day workflow. Virtual supervision is not just a technology shift—it’s a care delivery model. And it only works if every piece is aligned.
That’s where Tether Supervision comes in.
We’ve built our model specifically around contrast supervision in real-world imaging environments. Our radiologists are trained not just to “be available,” but to actively supervise—providing immediate, clear, and confident guidance during procedures, and stepping in decisively when it matters most. In the rare event of a contrast reaction, response time, communication clarity, and clinical leadership are everything. That’s the standard we operate to.
On the platform side, we’ve designed a system that fits seamlessly into the imaging center workflow. It’s simple to deploy, reliable under pressure, and structured around how teams actually operate—not how software thinks they should. Sessions are initiated quickly, communication is continuous, and escalation pathways are built in. No complexity, no friction, no ambiguity about who is responsible.
But the most overlooked piece—and often the most important—is training. Virtual supervision only works when technologists feel confident and supported. We spend significant time upfront ensuring teams are fully prepared, from contrast protocols to emergency response workflows to mock scenarios. That preparation shows up when it matters most—during real patient care.
Ultimately, HB 2113 creates the opportunity. Execution is what determines whether that opportunity translates into better access, safer care, and more stable operations.
Our role is to make that transition straightforward, so imaging centers can adopt virtual supervision not just compliantly, but confidently.
Key Takeaways
HB 2113 is now law. Washington has formally authorized virtual direct supervision for IV contrast procedures using real-time audio and video technology.
Effective mid-2026. The statute becomes operative approximately 90 days after legislative adjournment, establishing a clear legal pathway for implementation.
DOH rulemaking is the next step. The Department of Health is expected to update administrative rules to align with the new statute, a process that may take 6–12+ months.
Statute governs in the interim. Imaging centers may begin implementing compliant virtual supervision programs once the law is effective, even as DOH guidance evolves.
On-site clinical readiness remains required. Facilities must continue to maintain trained personnel and emergency response capabilities at the point of care.
Adoption will vary. Some organizations will move quickly to capture operational and access benefits, while others may wait for additional regulatory clarity.
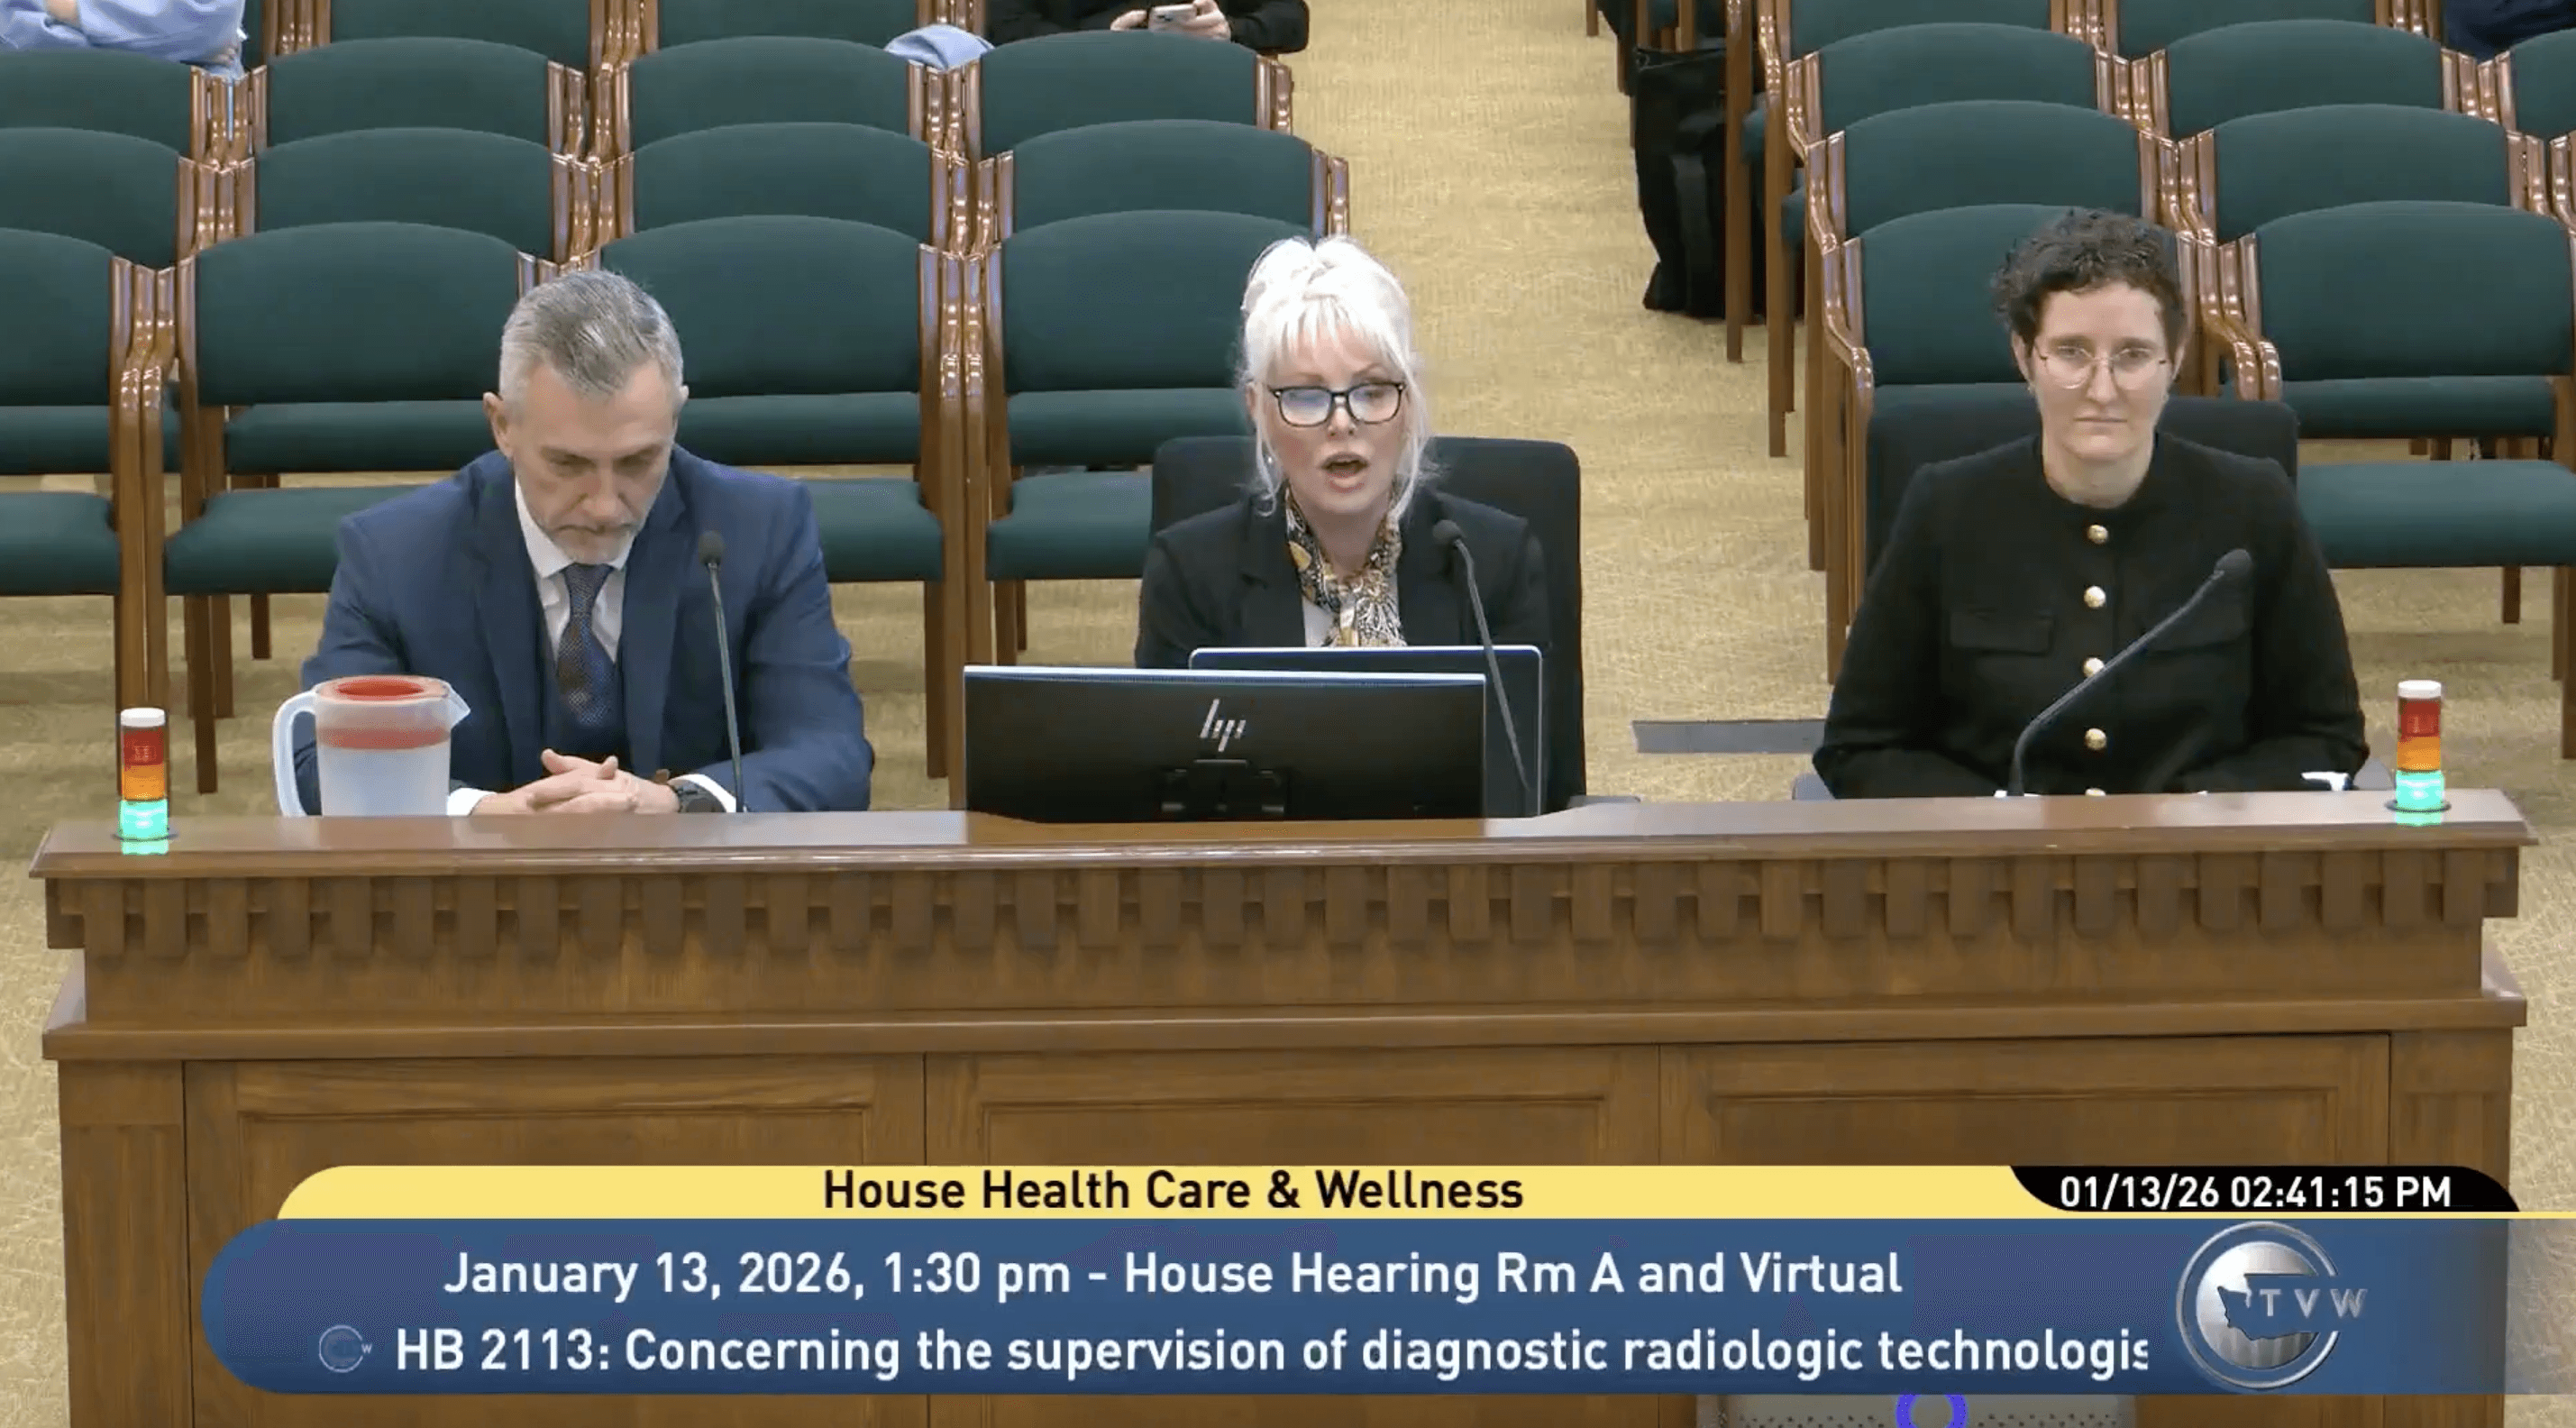
Washington State Bill Signals a Major Shift in Radiologic Technologist Supervision: HB 2113
In January 2026, Washington State Representative Andrew Engell (R-Colville) introduced House Bill 2113, a proposal that would modernize how radiologic technologists are supervised when administering intravenous (IV) contrast and performing certain diagnostic and therapeutic procedures. While the bill is state-specific, its implications extend far beyond Washington, offering a clear signal of where supervision policy is heading nationwide.
At its core, HB 2113 seeks to align statutory language with real-world clinical practice, advances in technology, and long-standing workforce realities in radiology departments and outpatient imaging centers.
What HB 2113 Proposes
Under current Washington law, many radiologic procedures involving injections require direct, in-person physician supervision, even when the technologist is highly trained and experienced. HB 2113 would update that framework by allowing greater flexibility while preserving patient safety safeguards.
Specifically, the bill would permit:
• Diagnostic radiologic technologists
• Therapeutic radiologic technologists
• Magnetic resonance imaging (MRI) technologists
to administer IV contrast under one of the following supervision models:
Real-time, two-way audio and video supervision by a physician, or
Direct supervision by an Advanced Registered Nurse Practitioner (ARNP) or Physician Assistant (PA)
This approach reflects how many imaging departments already operate, particularly in high-volume hospital systems and rural or underserved areas.
Key Safeguards Built Into the Bill
Importantly, HB 2113 does not loosen standards indiscriminately. The proposed language is explicit about safety, scope, and accountability.
The bill requires that:
Virtual supervision must include live, interactive audio and video-audio-only supervision is not permitted
Appropriately trained clinical staff must be physically present at the facility to respond to adverse contrast reactions
All procedures must remain within the supervising practitioner’s licensed scope of practice
The bill does not permit unsupervised administration of contrast
Existing safety protocols and professional standards may not be bypassed or weakened
In other words, HB 2113 does not remove supervision, it modernizes how supervision is delivered.
Why This Matters: Codifying Existing Practice
Rep. Engell has emphasized that the bill is not radical, but corrective.
“It is a common-sense bill that codifies existing practice that has been deemed, first by a lawyer and then by the agency, to be out of compliance with the law.”
Across the country, imaging centers have increasingly relied on remote physician availability, advanced practice providers, and structured escalation protocols to manage contrast administration safely, particularly as radiologist shortages intensify and demand for imaging continues to rise.
In many cases, the law simply has not kept pace with clinical reality.
Workforce, Access, and Cost Implications
HB 2113 also addresses several practical challenges facing healthcare systems:
1. Radiologist Shortages
Requiring on-site physician presence for every contrast study is increasingly impractical, especially in rural hospitals and outpatient centers with limited staffing.
2. Operational Efficiency
Rigid supervision rules can lead to:
Delayed exams
Canceled studies
Underutilized scanners
Increased labor costs
Modern supervision models allow centers to maintain throughput without compromising safety.
3. Career Mobility for ARNPs and PAs
The bill formally recognizes what many hospitals already acknowledge: trained ARNPs and PAs are qualified to supervise contrast-enhanced CT and MRI studies within defined protocols.
As Rep. Engell noted, without statutory clarity, healthcare organizations incur unnecessary costs and providers lose opportunities they have held for decades.
Alignment With Broader National Trends
While HB 2113 is a Washington bill, it mirrors broader developments across the U.S.:
CMS has increasingly acknowledged virtual direct supervision in certain contexts when real-time interaction is available
States are revisiting radiologic technologist scope-of-practice statutes that were written long before modern telehealth and secure video platforms existed
Accrediting bodies and health systems are focusing less on where a supervisor is located and more on availability, responsiveness, and escalation readiness
Washington’s proposal reflects a growing consensus: patient safety is driven by structured oversight and rapid clinical response, not physical proximity alone.
What This Means for Imaging Centers
If enacted, HB 2113 would give imaging centers in Washington:
Greater flexibility in staffing models
Clear statutory authority for virtual physician supervision
Reduced risk of technical non-compliance
A framework that supports consistent, scalable operations
More broadly, it provides a blueprint other states may follow as they reassess supervision laws in light of modern clinical workflows.
HB 2113 represents a thoughtful evolution of radiologic supervision policy. Rather than lowering standards, the bill clarifies expectations and legitimizes supervision models that are already widely used and clinically accepted.
As more states confront similar pressures, legislation like HB 2113 underscores an important shift: the future of radiologic supervision is structured, accountable, and increasingly virtual by design, not by exception.
At Tether Supervision, we closely monitor state-level regulatory developments like HB 2113 as part of our commitment to compliant, high-reliability supervision models. Clear legislation enables imaging centers to adopt modern workflows with confidence, without compromising safety or care quality. For more information, see our updated virtual contrast supervision policy & regulation tracker.

CMS Contrast Supervision Requirements in 2026: What Imaging Centers Need to Know
When it comes to healthcare, regulatory compliance is essential, particularly for procedures involving contrast media in diagnostic imaging. The Centers for Medicare & Medicaid Services (CMS) sets forth guidelines to ensure patient safety and quality care during contrast administration. For radiology practices, hospitals, and imaging centers, grasping these supervision requirements is key to staying compliant and optimizing patient outcomes. At Tether Supervision, we’re here to unpack these guidelines and demonstrate how our solutions align seamlessly with CMS standards.
Read about all of the policies from the ACR, CMS, and beyond in the Tether Supervision Contrast Supervision Policy Tracker.
CMS Direct Supervision Summary (2026)
Most contrast-enhanced CT and MRI exams require direct supervision.
CMS allows virtual direct supervision through December 31, 2025. A permanent rule for diagnostic tests takes effect January 1, 2026 allowing virtual oversight.
Supervising physicians must be immediately available and trained for the procedure.
Documentation of supervision method, availability, and interventions is required for Medicare reimbursement.
Tether Supervision provides CMS-compliant real-time radiologist oversight for contrast exams, trusted by 85+ imaging centers and backed by more than 45,000 supervised hours.
What do CMS guidelines require for supervision of contrast media?
CMS defines three levels of supervision for services performed by technologists or auxiliary personnel. General supervision allows oversight without the physician being on-site. Direct supervision requires the physician to be immediately available in the facility or connected virtually through real-time audio and video technology. Personal supervision requires the physician to be physically present in the same room.
For nearly all contrast-enhanced CT and MRI services, CMS requires direct supervision. The supervising physician must be able to intervene immediately and must have the training to oversee contrast administration safely. These requirements apply across outpatient imaging centers, hospital outpatient departments, and independent diagnostic testing facilities.
How did direct supervision evolve from in-person to virtual?
In the early years of advanced imaging, CMS required strict on-site presence for tests involving contrast. When CT and MRI adoption grew in the 1990s, concerns about contrast safety led CMS to mandate physical presence for Level 2 diagnostic tests. IDTFs faced especially rigid requirements and typically needed on-site radiologists for all contrast procedures.
By the 2010s, reaction rates had declined, training improved, and real-time communication technology had matured. The shift toward virtual guidance began gaining acceptance. The COVID-19 Public Health Emergency accelerated this trend. CMS revised the definition of direct supervision in 2020 to permit virtual presence through live audiovisual technology. This update maintained safety while addressing nationwide staffing shortages. The model worked well enough that CMS extended virtual supervision beyond the end of the PHE.
CMS finalized the 2025 Medicare Physician Fee Schedule on November 1, 2024 and extended virtual direct supervision for most outpatient services through December 31, 2025. In addition, CMS created a permanent rule that begins January 1, 2026 for diagnostic tests. These tests may be supervised virtually using real-time two-way audiovisual technology. This marks a significant policy shift that recognizes the role of technology in strengthening clinical oversight.
Why does direct supervision matter so much for contrast-enhanced imaging?
Contrast agents improve diagnostic accuracy but introduce risks such as allergic reactions and hemodynamic instability. The American College of Radiology reports a 1 to 2 percent overall reaction rate, with a small subset requiring urgent intervention. Direct supervision ensures that a qualified physician can guide technologists in real time.
Supervision also protects Medicare reimbursement. Claims submitted without the correct level of supervision are vulnerable to denials, audits, and repayments. Imaging centers that do not maintain reliable supervision systems often cancel exams unnecessarily, lose revenue, and risk non-compliance.
What are the CMS direct supervision standards? How does it work?
CMS direct supervision rules require that contrast administration be performed by qualified clinical staff while a supervising physician remains immediately available to assist. Technologists or nurses who administer contrast must be properly trained and operate under the oversight of a physician who can intervene at once if a reaction occurs. Under current CMS policy, this presence can be physical or virtual through real-time audio and video technology permanently beginning January 1, 2026.
To stay compliant, imaging centers must maintain accurate documentation of who supervised each exam, how supervision was provided, and whether the supervising practitioner was continuously available. Facilities must also have emergency protocols and equipment in place, including crash carts and trained personnel, to manage adverse reactions under the direction of the supervising physician. These standards protect patient safety and determine whether Medicare will reimburse contrast-enhanced diagnostic imaging.
What were the traditional in-person supervision standards?
Before the pandemic, direct supervision required the supervisor to be physically in the same department or office suite where the procedure occurred. They needed to be able to intervene at once if needed. Practices had little flexibility in how they structured coverage, and staffing gaps commonly created delays or cancellations.
Which services specifically require direct supervision?
Understanding which services fall under the direct supervision requirement is essential for compliance and correct billing.
Incident-to services
Incident-to services are performed by auxiliary personnel and are billed under a physician’s NPI. Direct supervision is required for Medicare to reimburse these services at 100 percent of the physician fee schedule. Without direct supervision, reimbursement defaults to the lower non-physician practitioner rate.
Diagnostic tests and procedures
Many diagnostic tests require direct supervision. This includes certain ultrasound procedures, fluoroscopy, and moderate complexity laboratory tests. The supervising physician must have the appropriate training for the specific exam. IDTFs must meet additional requirements to ensure staff qualifications.
Setting-specific rules
Physician office settings require the supervising physician to be in the office suite and immediately available. Hospital outpatient departments allow the supervising practitioner to be available within the hospital campus or provider-based department. Rural health clinics and federally qualified health centers operate under different supervision frameworks that account for staffing realities. Home health has its own separate certification and review standards.
What compliance pitfalls should providers avoid?
Common errors include assuming general supervision is sufficient, billing incident-to services without direct supervision, and failing to document the supervising practitioner’s availability. Some organizations use technology that does not meet CMS standards, assign too many concurrent procedures to one supervisor, or misunderstand how rules vary by setting. Routine audits focused specifically on supervision help prevent these issues.
How Tether Supervision Supports CMS Compliance
Navigating CMS rules can be daunting, especially for resource-limited facilities. Tether Supervision offers a telemedicine platform connecting your practice with board-certified radiologists for real-time, remote supervision—fully compliant with CMS’s direct supervision standards, including the 2025 virtual extension. Benefits include:
Instant Radiologist Access: Our network ensures supervision is always available.
Workflow Integration: Our technology streamlines operations for technologists and staff.
Cost Efficiency: Meet CMS requirements without hiring additional on-site radiologists.
How long will virtual direct supervision be available?
CMS has created two timelines. For diagnostic tests, a permanent rule takes effect January 1, 2026 that permits virtual direct supervision using real-time two-way audiovisual technology. For other outpatient services, the temporary flexibility continues through December 31, 2025 and is aligned with telehealth policy updates. Virtual direct supervision requires real-time, interactive communication between the supervising practitioner and the personnel performing the service.
Read more about the permanent virtual contrast supervising physician fee schedule.
What benefits does virtual direct supervision offer?
Lower staffing costs with more predictable coverage
Centers avoid the cost of hiring additional on-site radiologists to meet direct supervision requirements. Virtual workflows provide predictable, scalable coverage that aligns with demand without unnecessary labor expense.
Strengthening physician capacity and reducing burnout
Remote supervision allows physicians to oversee multiple sites without traveling between facilities. This improves physician efficiency, reduces burnout, and prevents coverage gaps that commonly lead to delayed exams or canceled appointments. Imaging centers maintain continuous supervision even during staffing shortages or unpredictable scheduling needs.
Fewer cancellations and smoother imaging workflows
With virtual supervision available at all operating hours, technologists no longer need to postpone or reschedule contrast exams due to missing on-site coverage. This prevents revenue loss, shortens wait times, and keeps schedules on track.
Expanded access to care
Virtual supervision increases access to diagnostic imaging in rural and underserved areas that struggle to recruit on-site radiologists. Patients with transportation or mobility challenges can receive contrast-enhanced CT or MRI closer to home while still benefiting from real-time physician oversight. This supports health equity and improves continuity of care.
See how Tether Supervision expanded access in rural West Texas.
Stronger regulatory compliance and audit readiness
Virtual direct supervision solutions that track supervision availability and communication improve documentation for CMS audits. Reliable real-time oversight supports compliance with federal supervision rules and ACR practice parameters.
Improved patient experience and confidence in care
Patients benefit from timely exams, fewer delays, and the reassurance that a supervising radiologist is available during contrast administration. This builds trust and strengthens the center’s reputation for safety and quality.
What technology is required for CMS-compliant virtual direct supervision?
Real-time two-way audio and video communication is required. Telephone-only communication, one-way video feeds, and delayed review do not meet CMS standards.
Does direct supervision require the physician to be in the same room?
No. Under the traditional definition, the supervising practitioner must be present in the office suite or department and immediately available. Under the current extension, this requirement can also be satisfied through real-time virtual presence.
What documentation is needed to prove supervision occurred?
Documentation should include the supervising practitioner’s name, credentials, NPI, time of supervision, confirmation of immediate availability, whether supervision was in-person or virtual, and any interventions. For virtual supervision, documentation must also include the specific technology used and confirmation that continuous audiovisual connection was maintained.
How does Tether Supervision support CMS compliance?
Tether Supervision enables imaging centers to meet CMS direct supervision requirements through real-time radiologist oversight for contrast-enhanced CT and MRI exams. Our platform is fully aligned with CMS’s current rules, including the extension of virtual direct supervision through 2025 and the permanent diagnostic test supervision rule that begins in 2026. With coverage trusted by more than 85 imaging centers nationwide and over 45,000 hours of contrast supervision completed, Tether provides the scale and reliability needed to stay compliant every day of the year.
Imaging centers gain immediate access to board-certified radiologists who remain available throughout the procedure, ensuring the required supervision level for Medicare-billable services at all operating hours. Our integrated audiovisual workflows help technologists avoid delays or cancellations and maintain clean documentation that supports CMS audit readiness. Practices also reduce staffing costs by replacing expensive on-site radiologist coverage with predictable, compliant virtual supervision that keeps schedules running smoothly.
Best Contrast Supervision Practices for Radiology Teams
Align with CMS and optimize your process with these tips:
Regular Training: Keep staff updated on contrast protocols and reaction management.
Adopt Technology: Use solutions like Tether Supervision to bridge staffing gaps.
Audit Policies: Routinely check supervision and documentation practices.
Educate Patients: Explain contrast use and safety measures to enhance trust.
The Future of Contrast Supervision
CMS contrast supervision requirements continue to evolve, and 2026 marks a turning point in how direct supervision is delivered. Virtual supervision has proven effective for safety, access, and operational efficiency. Facilities that adopt compliant virtual workflows now will be well positioned for the permanent CMS changes ahead. Tether Supervision provides the real-time oversight, documentation support, and regulatory alignment needed to meet CMS expectations with confidence.
More than 85 imaging centers have used Tether Supervision for 45,000 hours of safe, CMS-compliant contrast oversight. Schedule a demo to see how virtual direct supervision integrates into your workflow.